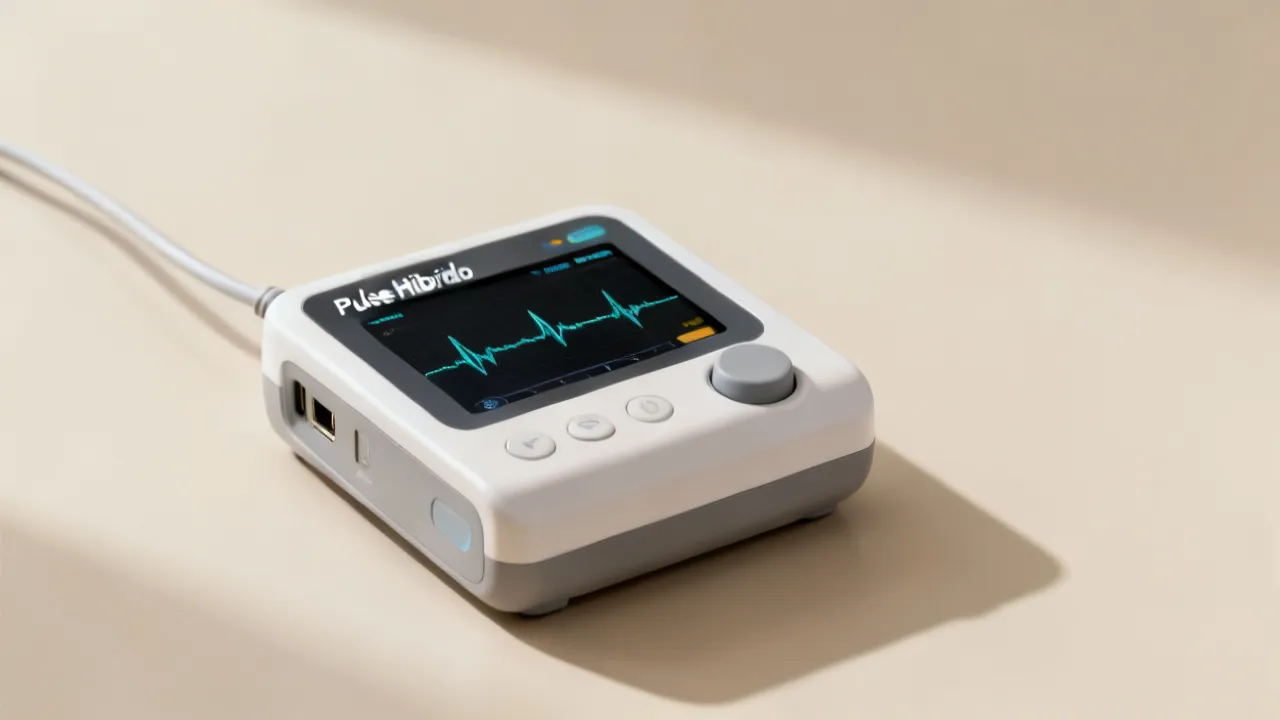
Pulse Hibrido: Technical Guide for Medical Users
Pulse Hibrido systems are hybrid pulse technologies used for targeted therapeutic stimulation, typically requiring careful selection of parameters and compatible hardware. This guide explains what “Pulse Hibrido” generally refers to in clinical contexts, outlines selection and safety considerations, and offers an objective decision framework. It also provides conditions, supplier considerations, and practical FAQs to support responsible implementation.
1) Key considerations for Pulse Hibrido selection and use
Pulse Hibrido refers to a hybrid pulse approach used in therapeutic and rehabilitation contexts, where stimulation characteristics are combined (for example, blended waveform strategies and/or coordinated delivery modes). In practice, successful deployment depends less on marketing terms and more on verified device specifications, appropriate clinical indications, patient tolerance, and strict operational controls. If you are evaluating a Pulse Hibrido system for a clinic, facility, or research workflow, prioritize documented waveform details, safety limits, documented treatment modes, and a clear protocol that aligns with your use-case.
Because hybrid pulse concepts can be implemented in multiple ways across product families, “Pulse Hibrido” should be treated as a functional descriptor rather than a single universal technology. The very reliable buying decision comes from comparing technical documentation (waveform, duty cycle, pulse width/rate ranges, output stability, and contraindication notes) and confirming that the supplier can provide traceable documentation and service support.
When people hear “hybrid,” they often assume it means “more advanced” or “better.” In healthcare technology procurement, however, “hybrid” is not automatically synonymous with “superior.” Hybridization can mean different things: one device might blend two waveforms within a single session, another might switch between modes across time blocks, and another might apply layered effects across channels. Each of those approaches can produce different patient sensations, different skin/interface responses, and different safety considerations. Therefore, it is essential to define what “hybrid” means operationally for the exact model you are considering.
Additionally, selection is not only a technical decision. Hybrid pulse devices can affect staffing patterns (e.g., time required for setup, electrode application checks, documentation, and troubleshooting). They can also influence throughput, because some interfaces require careful placement, skin conditioning, or specific lead management. In many facilities, the “real” total cost includes staff time and operational complexity. So when you evaluate Pulse Hibrido selection, treat it as an integration project: clinical fit, engineering fit, workflow fit, and governance fit—together.
A strong selection process also clarifies the measurement of success. Outcomes may include patient-reported comfort, adherence to the intended protocol, reduction in session cancellations, improved functional metrics (depending on indication), and consistent documentation quality. Many adoption failures are not due to the device output itself, but due to mismatches between the device’s capabilities and the site’s protocol design, staffing capacity, or patient population characteristics.
2) What “Pulse Hibrido” generally means in hybrid pulse technology
In the medical-device ecosystem, pulse-based therapies typically deliver electrical or electromagnetic stimulation in controlled pulses. The term Pulse Hibrido is commonly used to describe a hybrid strategy—meaning more than one stimulation behavior is combined within a therapeutic concept. Depending on the manufacturer, that “hybrid” may involve one or both of the following:
- Waveform hybridization: combining characteristics of different pulse shapes or delivery patterns to target specific therapeutic goals (e.g., comfort, tolerability, tissue response modulation).
- Operational hybridization: combining modes of delivery (such as intermittent and sequential strategies), sometimes coupled with parameter switching across treatment phases.
From an industry-expert perspective, the practical question is not “Is it Pulse Hibrido?” but “What hybrid pulse behavior does this particular device actually produce?” Two systems marketed with the same name can implement meaningfully different output profiles and safety boundaries. For objective evaluation, request the manufacturer’s waveform documentation and output specifications, ideally supported by compliance evidence.
To make this evaluation concrete, consider how “hybrid” can show up in real-world control terms. For example:
- Within-session blending: The device may deliver waveform A for a defined portion of the session (e.g., first 10 minutes) and then waveform B for another portion. This can influence comfort over time and affect how clinicians interpret patient response.
- Within-cycle mixing: Some hybrid concepts might interleave micro-behaviors at short time scales (e.g., alternating stimulation polarities or changing rise/fall characteristics frequently). This may require more detailed documentation because the effective stimulation pattern experienced by tissue and the skin interface can be less intuitive.
- Multi-channel choreography: If the device has multiple channels, hybrid behavior might be coordinated across them. That coordination affects not only safety but also how clinicians interpret multi-site symptoms or functional responses.
- Parameter-switching algorithms: A device might automatically adjust amplitude or other parameters within safe bounds based on preset rules or feedback signals. Even if it is not fully closed-loop, these internal rules must be understood for protocol consistency.
Because terminology can vary across regions and specialties, facilities should avoid assumptions and instead align the system’s intended use with their protocols. If your clinical governance requires evidence of specific stimulation characteristics, you should treat the device’s “hybrid pulse behavior” as a key part of the validation package—similar in importance to electrode compatibility and safety features.
In short, “Pulse Hibrido” typically means “hybrid pulse behavior exists,” but the exact implementation is model-specific. The decisive factor is not how the concept is named; it is how it is delivered.
3) Why parameter transparency matters more than brand labels
Pulse therapies are sensitive to parameter choices. Even small differences in pulse width, amplitude calibration method, repetition frequency, rise/fall characteristics, and switching timing can change the stimulation experience and safety profile. Therefore, when assessing a Pulse Hibrido system, it is essential to verify:
- Output control method: whether the device uses closed-loop control (where applicable) or relies on open-loop settings.
- Parameter resolution and repeatability: how precisely clinicians can set and reproduce the same treatment parameters across sessions.
- Electrode/interface compatibility: whether the system is designed for specific electrode types, sizes, and placement protocols.
- Safety interlocks and limits: overcurrent/overvoltage protections, compliance limits, and session termination behavior.
In professional settings, the “right” system is the one that enables repeatable clinical protocols with clearly documented boundaries—not simply the one with the broadest list of modes.
Parameter transparency matters because hybrid pulse systems may create “non-obvious” behavior. For example, a device could list a “comfort mode” that appears gentle due to a label, but the underlying switching logic might still create peak electrical stresses at the interface. Conversely, a device could appear more complex but might implement hybridization in a way that improves patient comfort while staying within conservative safety boundaries. Without parameter transparency, you can’t objectively compare devices.
To make parameter transparency actionable, clinics often build a simple “spec review worksheet.” For each candidate device, they fill in values for:
- Primary waveform type(s) used in the hybrid strategy (and how they change over time).
- Pulse width range and repetition rate range.
- Amplitude or intensity control method, including how intensity corresponds to measurable output (e.g., current into specified load, voltage under load constraints, or other defined units).
- Duty cycle and switching timing (especially important when the device changes from one sub-mode to another).
- Output stability and what happens when electrode contact changes (e.g., does the device limit output, pause, or simply continue?).
- Operational limits: maximum session duration, maximum number of sessions, maximum ramp-up/ramp-down behavior, and inter-session constraints if applicable.
- Device behavior on fault detection: does it stop safely, alert staff, require manual acknowledgment, or automatically reduce output?
This worksheet becomes an internal reference that clinicians and engineers can use during setup and troubleshooting. It also strengthens procurement documentation by ensuring the buying decision is grounded in verifiable behavior.
Finally, transparent parameters enable post-market learning. If a site discovers that a certain patient group experiences discomfort, the site can review whether the discomfort correlates with specific parameter ranges or specific hybrid switching phases. Without transparency, troubleshooting becomes subjective and slower.
4) Where Pulse Hibrido systems are commonly considered
Pulse-based therapeutic systems may be considered in fields such as rehabilitation, pain management workflows, neuromuscular conditioning, and certain physiotherapy regimens—always under appropriate clinical oversight and with adherence to local clinical guidelines and the manufacturer’s intended use statement. Because terminology can vary across regions and specialties, facilities should avoid assumptions and instead align the system’s intended use with their protocols.
Also note that many treatments using pulse devices require a patient-specific approach. Clinicians typically account for factors such as skin sensitivity, electrode tolerance, comfort goals, baseline conditions, and contraindication screening. A robust Pulse Hibrido evaluation includes not only the device features, but also the clinical workflow: assessment, parameter selection, monitoring, and documentation.
In practical adoption, facilities often encounter different patient realities that affect how hybrid pulse devices should be implemented. For instance:
- Comfort thresholds vary widely: Even within the same clinical indication, patients can have different pain sensitivity and different skin reactivity. Hybrid switching might help some patients but overwhelm others if the transitions are not carefully controlled or if ramp-up is not gradual.
- Skin/interface conditions are not uniform: Hydration level, hair density, callus thickness, scar tissue, and adhesive response can all influence electrode contact quality. The device’s reaction to contact variability—whether it maintains output, limits output, or pauses—is critical.
- Functional limitations affect placement reliability: If a patient cannot maintain positioning, electrode placement stability may degrade mid-session. The device should have adequate interface monitoring, but the clinic must also establish a positioning protocol.
- Clinician experience changes outcomes: Protocol adherence, correct setup order, and patient education strongly influence comfort and safety. Hybrid pulse devices can be more sensitive to setup errors if hybrid behavior depends on precise parameter ranges.
Because of these factors, “where Pulse Hibrido systems are commonly considered” is less important than “how Pulse Hibrido systems can be used safely and consistently within your specific patient population.” Procurement should therefore include a realistic workflow plan: how staff will screen patients, apply electrodes, verify contact conditions, and respond if discomfort is reported.
Some facilities also treat hybrid pulse devices as part of a multi-modal plan (e.g., combining stimulation sessions with exercises, manual therapy, education, or other rehabilitation tools). In that case, scheduling and sequencing matter. If hybrid pulse sessions affect muscle tone temporarily, the clinic must decide how to integrate them with later physical activity. That integration is a clinical protocol issue, not a device feature issue.
5) Pricing: how to evaluate cost without sacrificing quality
You may encounter different pricing structures when buying a Pulse Hibrido system. Some providers focus on the base device, while others bundle accessories, consumables (such as electrode interfaces), training, or maintenance coverage. Even when a supplier offers a “starter package,” the real cost is the total cost of ownership—especially if your clinic expects regular throughput.
To evaluate price objectively, separate components into categories:
- Device cost: includes the main console and core output module.
- Accessories: electrode/interface types, leads, adapters, electrode holders, and replacement items.
- Service and calibration: warranty terms, planned maintenance, replacement lead times, and service availability.
- Training and documentation: clinical training sessions, user manuals, protocol guides, and risk documentation support.
- Software/service subscription (if applicable): updates, parameter libraries, or device management tools.
Industry practice: In regulated or high-stakes contexts, the lowest initial price can introduce hidden costs—such as reduced service responsiveness, limited compatibility, or insufficient documentation for safe operation. Conversely, the highest price does not automatically indicate better outcomes; it may include broader service coverage or more elaborate hardware. The goal is cost-to-capability alignment.
If you have specific price data, supplier names, or a location-specific offer, you can incorporate them into a structured comparison. In this draft, pricing and supplier specifics were not provided, so the top approach is a methodology for evaluating them rather than repeating unverified numbers.
To go beyond generic cost evaluation, many facilities build a “minimum service level” requirement into procurement. This might include:
- Maximum expected turnaround time for repairs (and what happens if replacement hardware is not available).
- Availability of loaner units or expedited service for urgent downtime scenarios.
- Availability and pricing of spare parts (electrodes/leads/connectors) and lead times for replacement.
- Whether calibration is required periodically and how calibration is scheduled to avoid operational downtime.
In hybrid pulse deployments, continuity of care matters because protocols often depend on consistent device performance. If the device requires frequent recalibration or service to maintain output stability, that can affect session outcomes and patient confidence. Therefore, pricing evaluation should explicitly include output stability and service plan assumptions—rather than treating stability as a “given.”
Another cost factor is documentation. Sometimes the hardware price is similar across vendors, but one vendor provides better protocol documentation, clinician training materials, and safety guidance. Those documentation differences can reduce training time and reduce operational risk. In many clinics, that value is not captured in the initial quote, but it impacts time-to-competency and reduces the chance of protocol errors.
Finally, consider how costs scale. If your facility expands patient volume, do you need additional channels, extra units, more electrode kits, or more staff training? A device might be affordable when purchased alone, but if it requires high per-session consumables or frequent lead replacements, the ongoing cost may be significantly higher. Evaluate cost per session as part of the procurement model when possible.
6) Supplier and documentation checklist for Pulse Hibrido buyers
When selecting a supplier for a Pulse Hibrido system, experienced facility managers and clinical engineers commonly request the following:
- Intended use statement and user classification (where applicable in your regulatory context).
- Technical specifications describing the hybrid pulse behavior (waveforms, output ranges, parameter limits).
- Safety and contraindication information in plain language and clinician-facing formats.
- Quality and compliance evidence (e.g., applicable conformity documents for regulated markets).
- Installation and maintenance plan, including warranty coverage and recommended service intervals.
- Service accessibility (repair turnaround expectations, spare parts availability, escalation path).
From a procurement standpoint, you want a supplier who can provide traceability and support for safe use, rather than only a quick quotation.
It is often helpful to treat documentation as part of the product. For a hybrid pulse device, key documentation deliverables may include:
- Clinician user manual: includes setup steps, electrode/interface requirements, parameter selection, safety warnings, and fault responses.
- Technical reference: includes waveform descriptions, pulse characteristics, switching logic explanation, and output specification methodology.
- Risk management summary: in regulated contexts, the supplier may provide information on hazards and controls relevant to clinical use.
- IFU contraindication lists: should be accessible and consistent with the intended use.
- Training materials: slides or written modules that help staff learn the correct protocol flow and safe responses to patient discomfort.
- Service manual or service procedures (as applicable): for technical staff or authorized technicians.
Also consider whether the supplier can provide “validation-ready” content. For instance, a facility may need evidence that the device output behaves consistently across permitted settings. If you require internal validation or acceptance testing, the supplier should be willing to provide guidance on what should be tested and how to interpret results.
Some suppliers can also help with a site acceptance checklist. That checklist can include basic operational checks, electrode detection checks, verification of alarm behavior, and confirmation that device settings replicate correctly. These are not always required, but having a structured acceptance approach often reduces early deployment errors.
Finally, evaluate the supplier’s long-term posture: do they support updates, how they handle firmware/software changes, and whether those changes affect waveform behavior. Hybrid pulse devices might evolve through firmware updates; if waveform switching logic changes, clinicians need to know. Therefore, ask whether the supplier can provide change logs and whether updates require re-training or protocol review.
7) Conditions and requirements (comparison table)
The table below rephrases supplemental decision information into an operational comparison. Since no specific additional-information dataset was provided, the comparison focuses on universally applicable requirements for responsibly evaluating a Pulse Hibrido system.
| Evaluation area | What to confirm for Pulse Hibrido systems | Why it matters |
|---|---|---|
| Clinical alignment | Intended use statement matches your clinic protocol and patient population screening approach. | Ensures the device is used within stated boundaries and supports consistent documentation. |
| Hybrid pulse definition | Manufacturer clarifies what “hybrid” means for that model (waveform/mode behavior and switching logic). | Prevents mismatched expectations and reduces risk from unclear parameter behavior. |
| Safety features | Documented safety limits, session behavior, interface checks, and contraindication list. | Improves patient safety and clinician confidence during sessions. |
| Parameter repeatability | Controls provide consistent setpoints and predictable output across sessions. | Enables protocol fidelity and more reliable outcomes tracking. |
| Electrode/interface compatibility | Supported electrode types, interface conditions, and placement guidance. | Reduces variability and supports safe current density at the interface. |
| Training and documentation | Includes user training resources and clinician-friendly protocol guidance. | Supports correct usage and reduces operator variation. |
| Service and support | Warranty terms, service response expectations, and replacement parts availability. | Protects continuity of care and reduces downtime costs. |
To make the comparison even more operational, clinics often add a “go/no-go” threshold for each category. For example, if the supplier cannot provide waveform switching logic documentation, that device might fail the hybrid-definition criterion. Similarly, if the supplier cannot confirm electrode/interface compatibility for the electrodes your clinicians already use, it might fail the interface-compatibility criterion.
Because hybrid pulse systems can influence patient comfort and safety in subtle ways, it is appropriate to treat documentation quality as a safety factor—not just a purchasing convenience. In many projects, documentation gaps lead to longer training periods, more protocol uncertainty, and more patient complaints. Those issues can undermine patient trust and clinical adoption.
8) Step-by-step guide to vetting and implementing Pulse Hibrido
Below is a structured approach facilities commonly use to reduce operational risk when adopting hybrid pulse devices. Adapt the steps to your regulatory framework and internal governance.
-
Define the clinical use-case and target workflow.
Identify what sessions will involve Pulse Hibrido, who will operate it, and which patient groups you intend to include—then cross-check the manufacturer’s intended use. -
Request model-specific documentation.
Ask for technical specifications that explicitly describe the hybrid pulse behavior (waveform characteristics, parameter ranges, mode switching behavior). -
Validate interface compatibility.
Confirm that your electrode/interface types and placement guidelines are compatible with the device. If your clinic uses multiple electrode models, verify each one is supported. -
Perform a risk review with clinical and engineering stakeholders.
Review contraindications, skin risks, patient comfort considerations, and any interface-related hazards (including lead integrity and proper placement). -
Establish a protocol and parameter selection workflow.
Define how clinicians select baseline parameters, adjust within safe boundaries, and document session settings and patient response. -
Conduct supervised staff training.
Provide role-based training: device operation basics, protocol application, troubleshooting steps, and escalation procedures for unexpected patient reactions. -
Run a controlled pilot session set.
For early adoption, track comfort feedback, interface tolerance, and any operational inconsistencies across multiple sessions. -
Implement monitoring and documentation controls.
Use standardized forms or electronic templates to log key parameters, patient feedback, and any deviations from the protocol. -
Review outcomes and refine protocols.
Use objective session notes and clinician observations to decide whether parameter ranges or workflow steps should be adjusted within safe and approved boundaries.
To add practical depth, consider how to implement each step with measurable outputs. For example:
- Step 1 (Clinical use-case): Output could include an internal “patient eligibility criteria” document aligned with manufacturer contraindications, plus a mapping of the device modes to specific clinical goals (comfort, activation, pain modulation, etc.).
- Step 2 (Documentation request): Output could include a completed spec review worksheet capturing waveform switching logic, parameter limits, and device fault behavior.
- Step 3 (Interface compatibility): Output could include a validated list of approved electrodes/leads/adapters and a placement guide checklist for clinicians.
- Step 4 (Risk review): Output could include a risk register entry list for likely hazards: skin irritation, improper electrode placement, patient anxiety due to sensation, electrode detachment, and device output changes on contact loss.
- Step 5 (Protocol workflow): Output could include standard parameter titration steps, stop criteria (e.g., patient discomfort thresholds), and documentation requirements.
- Step 6 (Training): Output could include competency sign-offs, mock fault drills, and a quick-reference card for staff.
- Step 7 (Pilot sessions): Output could include data capture for comfort ratings, skin checks, adherence to parameter ranges, and any deviations logged.
- Step 8 (Monitoring/documentation): Output could include audit criteria and a method for reviewing outliers or patient complaints.
- Step 9 (Refine): Output could include a documented protocol revision process with approvals (clinical lead and governance as required).
This approach transforms adoption from a one-time purchase into a controlled implementation lifecycle. Hybrid pulse devices can then be used consistently across staff and across time, which improves both safety and clinical value.
9) Conditions/requirements for safe operation (practical checklist)
- Patient screening must occur before each session. Confirm contraindications as per the device documentation.
- Use only manufacturer-approved accessories and electrode/interface components. Compatibility affects safety and performance predictability.
- Maintain correct placement and interface contact. Improper placement can change effective stimulation at the treatment site.
- Follow the defined parameter boundaries. Do not exceed manufacturer-stated limits for amplitude, pulse settings, duration, or session frequency.
- Train staff on troubleshooting and emergency procedures. If the device reports faults or patient distress occurs, stop and follow the device manual process.
- Document settings and patient response consistently. Reliable records support clinical governance and quality improvement.
Because hybrid pulse strategies may involve parameter switching, “safe operation” also includes a specific clinical habit: clinicians should verify that the device has entered the intended phase of the treatment during transitions. For example, if a hybrid protocol switches from waveform A to waveform B after a set time, staff should understand what indicator displays confirm the transition. If the device provides alarms or status indicators, clinicians should be trained to interpret them.
Additionally, facilities should implement skin monitoring and electrode integrity checks. Even if a device includes interface monitoring, it does not replace clinical observation. A robust checklist often includes:
- Skin inspection before placement (redness, irritation, broken skin, infection signs).
- Proper electrode adhesion check before stimulation begins.
- Assessment during ramp-up (ensuring patient comfort and verifying no sudden pain signals).
- Periodic checks during longer sessions, particularly if hybrid switching creates different sensations.
- Post-session skin inspection and documentation of any irritation or transient discomfort.
Another important requirement is data integrity for session documentation. If the clinic uses electronic templates, ensure staff fields capture the parameters that truly matter to the hybrid behavior (not only the overall mode name). This reduces the risk of incomplete or misleading clinical records.
10) Expert perspective: common pitfalls in Pulse Hibrido deployments
From a clinical-technology adoption standpoint, several patterns repeatedly emerge when hybrid pulse devices are introduced:
- Overreliance on mode names. Clinicians may select “hybrid” modes by label without understanding parameter behavior. A mode name is not a substitute for waveform documentation.
- Insufficient protocol standardization. If each therapist improvises parameter selection, it becomes difficult to learn what works safely and consistently for your patient population.
- Neglect of interface quality control. Electrode cleanliness, lead integrity, and correct contact conditions strongly influence patient comfort and device stability.
- Service and downtime planning gaps. Clinics sometimes underestimate how much continuity of care matters during repairs or recalibration.
By treating Pulse Hibrido like a protocol-driven system rather than a standalone gadget, teams typically achieve smoother integration and safer operations.
It is useful to expand these pitfalls with examples, because they often look different in the field:
- Pitfall: “Preset mode = safe enough.” Some teams assume that if a mode is factory preset, it must be inherently safer. But presets can still deliver strong stimulation depending on how intensity is calibrated and how electrode contact behaves. The team should still follow contraindications and titration principles.
- Pitfall: “We only need the broad parameter range.” Clinicians sometimes focus on maximum intensity but ignore waveform switching behavior. In hybrid protocols, switching can be the key factor that changes comfort and response. That means the protocol should address transitions, not only peak settings.
- Pitfall: “Documentation is optional.” When clinics treat documentation as an administrative task rather than a safety requirement, they lose the ability to detect patterns. Over time, patient complaints and protocol adjustments become untrackable.
- Pitfall: “Electrode interchangeability.” Staff may substitute electrode types due to availability or cost. If the device is designed for specific electrode characteristics and load conditions, using non-approved electrodes can produce unpredictable outcomes and potentially affect safety margins.
- Pitfall: “Inadequate training for fault states.” Many devices have fault indicators or contact-loss behaviors. If staff are not trained to interpret them, they may override safety processes or continue sessions when a stop-and-check is appropriate. Fault drills should be included in training.
When avoiding pitfalls, it helps to establish “minimum competency requirements” for anyone who operates the device. That includes knowledge of setup sequence, contraindication screening, parameter selection steps, stop criteria, and documentation. In high-throughput settings, device operators may change over time; competency maintenance is an ongoing responsibility.
Another subtle pitfall is not aligning patient communication with hybrid behavior. Because hybrid modes can produce changes in sensation during a session, patients may interpret transition sensations as worsening pain or discomfort if they are not prepared. Clinics can reduce anxiety and improve tolerance by educating patients about what sensations to expect and how to report discomfort early.
11) Reliability, compliance, and evidence considerations
Pulse-based medical devices should be evaluated with attention to regulatory compliance and evidence quality. Because specific performance outcomes depend on the exact device model, pulse parameters, treatment protocols, and patient context, it is not appropriate to generalize results across all “Pulse Hibrido” products.
For background on how medical device evidence is evaluated and how safety/quality systems are expected to function, readers may consult broadly recognized standards and regulatory frameworks. For example, in the U.S., the FDA provides guidance on medical devices and safety considerations. In Europe, the EU medical device regulatory framework and quality management expectations are described through MDR-related guidance and harmonized standards. Quality management systems are widely anchored in ISO 13485 and related standards. These sources support the principle that device adoption should be evidence-informed and governed by documented quality controls.
Sources (for general regulatory and quality background): FDA (medical device overview and safety/quality resources), European Commission (medical devices framework and MDR overview), ISO 13485 (quality management systems for medical devices).
From a practical perspective, compliance and evidence considerations often show up as procurement requirements. These may include:
- Conformity evidence: For regulated markets, request confirmation of applicable conformity assessments, labeling, and documentation status (as required by your jurisdiction).
- Risk management alignment: Suppliers should be able to explain hazard controls relevant to clinical use—especially hazards associated with electrical stimulation and interface contact variability.
- Software/firmware change control: Ensure the supplier has a change control process and can provide information about updates that might affect stimulation behavior or clinical workflows.
- Verification and validation: Ask whether the supplier can provide information on how output specs are verified and how the device maintains performance stability within tolerances.
Evidence is also an important procurement dimension. In some markets, clinical evidence for particular stimulation parameters may be limited. Even when peer-reviewed literature exists, results may be parameter-specific. Therefore, clinicians should avoid using literature outcomes as a generic promise that “this hybrid approach works.” Instead, evidence should be evaluated for relevance to your intended protocol: parameters, mode switching logic, electrode type, and patient population.
For facilities that conduct research, evidence considerations become even more stringent. Hybrid pulse devices might be used in studies requiring protocol reproducibility and careful parameter documentation. In those cases, a facility should implement additional controls such as calibration verification, version-controlled protocol parameter sets, and consistent electrode manufacturing batch selection (if relevant).
Finally, consider evidence quality for safety outcomes. Patient safety is not only about whether the device “works,” but also about how it behaves under edge cases: electrode detachments, partial contact, patient movement, and unexpected patient discomfort. A supplier that provides clear fault behavior documentation supports evidence-informed clinical risk management.
12) FAQs about Pulse Hibrido
Q1: What exactly is Pulse Hibrido?
Pulse Hibrido typically describes a hybrid pulse therapeutic strategy within a device—where two or more stimulation behaviors are combined. The exact meaning varies by manufacturer, so you should confirm the model’s waveform and mode switching specifics in the technical documentation.
Q2: How do I compare Pulse Hibrido devices fairly?
Compare model-specific parameters (waveform characteristics, output ranges, parameter resolution, safety limits), interface/electrode compatibility, and the quality of documentation and service support. Avoid judging by mode names alone.
Q3: Does Pulse Hibrido guarantee better clinical outcomes?
No single label guarantees outcomes. Clinical results depend on correct indication, protocol design, parameter selection, and patient response. A hybrid pulse concept may improve tolerability or fit a protocol, but outcomes must be assessed within your clinical governance and documented workflows.
Q4: What should I check regarding safety?
Confirm contraindications and safety limits in the device manual, verify supported accessories, ensure staff training is documented, and establish a protocol for stopping therapy if the patient experiences discomfort or if the device reports faults.
Q5: Are there specific contraindications I should review?
Contraindications depend on the device and intended use. The manufacturer’s documentation should be treated as the primary source. Your clinicians should screen patients before each session according to that guidance and your internal policy.
Q6: How important is training for Pulse Hibrido use?
Training is essential. Even when devices are user-friendly, operator interpretation of parameter settings and electrode placement affects safety, comfort, and protocol consistency. A structured training plan typically reduces variability.
Q7: What role do suppliers play beyond the initial sale?
Suppliers should provide installation support (if relevant), documentation, training materials, service coverage, spare parts access, and an agreed process for repairs and maintenance. For protocol-driven use, documentation quality can be as important as the hardware itself.
Q8: Can I use any electrode with Pulse Hibrido?
No. Very pulse devices require manufacturer-approved electrode/interface types and placement conditions to ensure safe and predictable operation. Always confirm compatibility with the specific model.
Q9: Where can I find reliable information about device performance?
Start with manufacturer technical documentation, intended use statements, and safety information. For evidence quality, rely on peer-reviewed clinical literature tied to specific device parameters when available, and review general regulatory/quality frameworks to understand evaluation principles.
Q10: How should a clinic document Pulse Hibrido sessions?
Document parameter settings, session duration, electrode/interface types, patient comfort notes, and any deviations from protocol. Consistent documentation supports both clinical governance and ongoing protocol refinement.
13) Practical next steps
If you are actively evaluating Pulse Hibrido systems, the very productive next move is to request model-specific technical documentation and clarify what the hybrid pulse behavior actually entails. Then map that information to your clinic workflow: patient screening, electrode/interface compatibility, parameter selection rules, staff training, and service continuity. With that structure, you can compare suppliers and models objectively—even when marketing descriptions differ.
To make your next steps more concrete, you can create a short “information request packet” to send to suppliers. A strong packet typically asks for:
- Waveform and hybrid switching documentation for the exact model (including any within-session switching timing or multi-phase structure).
- Output range specifications and the meaning of intensity units (current/voltage or other defined measures) under specified load or electrode conditions.
- Safety limits and fault behavior: what happens on contact loss, overcurrent, or device faults.
- Approved electrode/interface list and any placement or skin preparation requirements.
- User manual and clinician quick-start guide versions suitable for staff onboarding.
- Service plan summary: warranty terms, service response expectations, calibration and maintenance schedule, and spare parts availability.
- Training options: whether supplier provides initial training, refreshers, and competency assessment or sign-off templates.
- Firmware/software update policy: whether updates affect waveform behavior and how change logs are communicated.
After receiving responses, you can score each candidate device using your internally defined criteria. It is important to weight criteria appropriately: for example, hybrid pulse definition clarity and safety documentation should carry more weight than the number of “named modes,” because those details directly affect patient safety and protocol reproducibility.
Optional: If you share the intended use (e.g., rehabilitation/pain workflow), your device requirements (number of channels, interface types), and any provided price/supplier details you want included, I can rewrite this article to integrate those specifics into a single procurement-ready narrative and a tighter comparison section.
-
1

A Guide to Cost-Efficient Small Electric Cars for Seniors
-
2
Mastering Debt Consolidation: Boost Your Credit Score and Manage Interest Rates
-
3
Your Guide to Loans, Credit Checks, and Interest Rates
-
4
Affordable Independent Living: Finding the Right Senior Housing
-
5
Guide to Senior Living Apartments: Affordable and Comfortable Environments